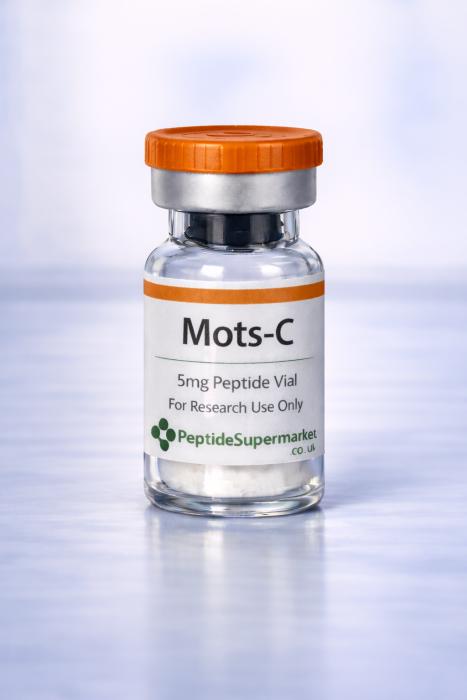
What MOTS-C actually is
MOTS-C is a 16–amino acid peptide encoded by mitochondrial DNA, specifically from a small open reading frame associated with the 12S rRNA region (in the way it’s commonly described).
Translation:
Your mitochondria—those “powerhouse organelles” people joke about—don’t just make energy. They send instructions.
MOTS-C is one of those instructions.
It’s a mitochondria-derived signaling peptide used for retrograde communication (mitochondria → nucleus).
Think of it like this:
Your cellular power plants don’t just produce electricity.
They also send a message to HQ about whether the whole city is about to brown-out.
MOTS-C is that message.
Why this matters: mitochondria don’t “just make ATP”
Most people only have one mitochondria sentence in their entire brain:
“Mitochondria make energy.”
True… and wildly incomplete.
Mitochondria also control:
inflammatory signaling
insulin sensitivity and fuel choice
oxidative stress load
cell survival vs cell death
tissue repair capacity
brain function (neurons are energy addicts)
So when mitochondria degrade, everything degrades.
That’s why “tired, inflamed, insulin resistant, foggy, not recovering” is not a personality flaw.
It’s an energy system problem.
The engine room: ATP and the Electron Transport Chain (ETC)
ATP is the currency. The ETC is the mint.
Inside the inner mitochondrial membrane you’ve got the classic line-up:
Complex I
Complex II
Complex III
Complex IV
Complex V (ATP synthase)
Electrons move through these complexes. Protons get pumped. A gradient builds—like water behind a dam.
ATP synthase is the turbine that cashes that gradient into ATP.
Here’s the ugly part:
Aging and chronic metabolic stress hammer Complex I first
When Complex I gets damaged, electrons leak.
Leaked electrons + oxygen = ROS (reactive oxygen species).
Then ROS damage the very machinery that’s already failing.
That’s the loop:
damage → leak → ROS → more damage → more leak → more ROS
That loop is mitochondrial dysfunction.
And mitochondrial dysfunction is the common denominator behind a lot of modern chronic disease patterns.
For a UK-only MOTS-C price comparison (so you can quickly compare listings), use our hub:
What MOTS-C is “for” in this framework
MOTS-C is portrayed as your mitochondria’s stress response signal.
When metabolic stress hits (overfeeding, under-sleeping, inactivity, oxidative load, injury, etc.), the “story” is:
mitochondria increase MOTS-C signaling
MOTS-C influences nuclear programs
the cell shifts toward repair + metabolic correction
It’s not a “stim” peptide. It’s a recalibration peptide.
The key pathway: MOTS-C → AMPK → PGC-1α
If you remember one chain, remember this one:
MOTS-C pushes AMPK
AMPK is the metabolic master switch. It’s what flips cells from:
store energy
touse energy efficiently and rebuild capacity
AMPK then upregulates PGC-1α.
PGC-1α is the “build more mitochondria” boss.
So the claimed magic isn’t just:
“MOTS-C gives you more energy.”
It’s:
MOTS-C triggers the program that makes better energy systems.
That includes:
improved mitochondrial biogenesis
improved energy efficiency
better fuel handling (especially glucose + fat oxidation dynamics)
The big misconception: “More ATP = more pep”
This is where people butcher the message.
Yes, MOTS-C is framed as supporting ATP production.
But the real pitch is metabolic efficiency and systemic regulation, not “caffeine but inside your cells.”
It’s the difference between:
giving a dying company a tiny cash infusion
vsreplacing the entire broken manufacturing line and fixing the supply chain
MOTS-C and the “Three Biological Failures” model
In your transcript, everything keeps coming back to the same triangle:
Systemic inflammation (the fire)
Insulin resistance (fuel can’t get where it needs to go)
ATP shortage (the power outage)
And the death spiral is:
inflammation damages mitochondria → ATP drops
low ATP worsens insulin signaling
insulin resistance increases inflammation
repeat until the system collapses into disease
Where MOTS-C plugs in (as framed in your script)
ATP shortage:
supports ETC efficiency (especially framed around Complex I stability/function)
promotes mitochondrial biogenesis via AMPK → PGC-1α
Insulin resistance:
AMPK activation shifts metabolism toward glucose uptake and fat oxidation
provides an “alternate glucose disposal” angle (insulin-independent uptake is the phrasing used)
Systemic inflammation:
suppresses inflammatory transcription signaling (you repeatedly mention NF-κB)
boosts antioxidant defense signaling (you repeatedly mention NRF2)
So MOTS-C is positioned as a “triangle solver,” not a single-symptom bandage.
Anti-inflammatory + antioxidant signaling (the “less shrapnel” effect)
You frame two big control nodes:
NF-κB = inflammatory transcription driver
NRF2 = antioxidant response driver
So the storyline becomes:
less inflammatory cascade ignition
more antioxidant production capacity
less oxidative damage to mitochondrial membranes and ETC complexes
better energy output per oxygen used
fewer downstream inflammatory triggers
It’s not “anti-inflammatory like an NSAID.”
It’s “change the upstream environment so the inflammatory cascade doesn’t keep re-triggering.”
What it means in real body systems
Brain
Neurons are energy-hungry and fragile. When mitochondria tank, neurons can’t maintain ion gradients, signaling, neurotransmitter cycling—everything gets sloppy.
Your script frames MOTS-C as relevant because it’s described as:
crossing into the CNS (in the narrative)
reducing neuroinflammatory activation (microglia emphasis)
improving neuronal energy availability
supporting plasticity signaling (BDNF gets mentioned)
Translation:
If the brain is running on a weak battery, you don’t “think harder.”
You fix the battery factory.
Heart + endothelium
The heart is an ATP furnace. Vessels are inflammation-sensitive.
You frame MOTS-C as helping via:
improved mitochondrial respiration in cardiac tissue
reduced inflammatory signaling in the heart
improved endothelial function via nitric oxide availability (in the narrative)
reduced foam-cell style plaque mechanics (via oxidized LDL uptake language)
Translation:
Don’t treat the heart like a plumbing problem.
Treat it like an energy system.
Kidneys
Proximal tubule cells are mitochondrial monsters because filtration and reabsorption are energy-expensive.
You frame MOTS-C as protective in kidney injury states because:
more ATP means pumps stay functioning
better hypoxia tolerance
better recovery after insult (ischemia/reperfusion emphasis)
Translation:
Kidney decline isn’t “normal aging.”
It’s often energy failure + inflammation + fibrosis mechanics.
Menopause (as you frame it)
You make the point that estrogen decline isn’t just “a hormone story,” it’s a metabolic shift because estrogen is mitochondrial-protective.
So in your framing, MOTS-C is positioned as:
restoring mitochondrial support that estrogen used to provide
improving metabolic rate, insulin sensitivity, cognitive fog, vascular function (in the narrative)
Translation:
Menopause symptoms can be downstream of mitochondrial stress—not just “low estrogen.”
Injury and repair
Repair is expensive. Tissue repair requires ATP for cell proliferation, ECM synthesis, immune cleanup, angiogenesis.
So in your framing:
MOTS-C speeds repair by powering the rebuild
reduces oxidative stress so less scar chaos accumulates
supports macrophage function (cleanup + transition into healing)
Translation:
You don’t heal faster by “wanting it more.”
You heal faster when the repair crew has power and materials.
The “why did it make me tired?” point
You included a useful interpretation:
Early fatigue can happen because the system may shift resources into repair programs—autophagy, mitochondrial quality control, cleanup—before the new “better mitochondria” capacity comes online.
In your framing:
“It didn’t drain you. It redirected you.”
Whether that’s what’s happening in any individual case depends on context—but as a narrative explanation, it’s coherent.
Before you buy MOTS-C, it’s worth checking a UK price comparison first. We keep a running list here:
Stacking logic: why you argue MOTS-C should come before SS-31
A very specific sequencing argument:
SS-31 is framed as optimizing/stabilizing existing mitochondria (cardiolipin support angle)
MOTS-C is framed as building/renewing the mitochondrial population (biogenesis + repair + cleanup)
So the recommended logic is:
Don’t polish a broken fleet.
Build a healthier fleet first—then upgrade it.
Meaning: MOTS-C first → then SS-31 makes more sense than the reverse.
Cycling and cautions (the “don’t be reckless” section)
You also make two important practical points:
1) Don’t run it indefinitely
The script frames the risk as:
constant external signal → downregulation/desensitization → diminishing returns
So the suggested structure in your narrative is something like:
a defined “on” block (weeks)
followed by an “off” block to resensitize and restore endogenous dynamics
2) Hard no zones (as you state it)
Your blanket rule in the transcript is basically:
pregnant / trying / breastfeeding → no peptides
because you’re not going to make the baby the experiment.
You also raise a caution about acute infection, with the idea that altering metabolism during active infection could theoretically cut both ways depending on context.
That’s not fearmongering—it’s just basic respect for complexity.
The clean conclusion
MOTS-C isn’t framed as a stimulant. It’s not framed as a “drug.”
It’s framed as:
a mitochondria-coded instruction set that pushes the body toward metabolic correction, better energy output, better insulin handling, and lower inflammatory signaling.
Or in the simplest possible language:
Your body doesn’t just need motivation.
It needs power plants that work.
Compare Mots-C prices across the UK
Side-by-side prices from every trusted UK supplier stocking Mots-C.


